SEARCH

Preset searches
PubMed -Respiratory medicine
Obstructive sleep apnoea hypopnoea
Tuberculosis primary care review
Upper respiratory tract infections
Lower respiratory tract infections
Practitioner 2011; 255 (1745):19-22
Improving outcomes in lung cancer patients
23 Nov 2011
AUTHORS
Dr David R Baldwin MD FRCP
Consultant Respiratory Physician, Respiratory Medicine Unit, David Evans Research Centre, Nottingham University Hospitals and Honorary Associate Professor, University of Nottingham
Article
Lung cancer is the leading cause of cancer mortality in the UK resulting in more than 33,500 deaths in 2008, 4,000 more than for bowel and breast cancer combined. Five-year survival figures are poor but have recently improved from around 5% to 7.5% in men and 8.5% in women.1
There is evidence of marked variation in the standard of care in England. Adjusted resection rates vary four-fold between cancer networks.2 It has recently been shown that if patients are first referred to a thoracic surgical centre, rather than a hospital that does not have thoracic surgeons on site, they are 51% more likely to have a resection.3 There are similar findings for other active treatments.4 By reducing this variation there is scope for marked improvement in outcomes, possibly to levels seen in other countries such as Australia, Canada, Sweden and Norway where five-year survival rates are approximately double.5 Thus there is a need to encourage lung cancer teams to select patients correctly so that the best treatment can be offered.
Improving diagnosis, staging and fitness assessment was a major focus in the recently updated NICE guideline on diagnosis and treatment of lung cancer, published in April 2011.6
The key recommendations in this partial update seek to ensure that:
• all multidisciplinary teams apply efficient and appropriate methods to diagnose and stage patients accurately
• fitness assessment is an objective process
• using accurate staging and fitness assessments, as many patients as possible are offered treatment with curative intent by recommending surgeons and clinical oncologists assess suitability for lung-sparing operations and radical radiotherapy
• patients receive information and support throughout the pathway through effective communication, supportive care and follow-up
• patients with small cell lung cancer (SCLC) are offered the most effective treatment
• patients are referred early for endobronchial treatment when appropriate
While improvements in these largely secondary care areas are essential, there are potentially more important and more difficult challenges for primary and integrated care. Almost three quarters of patients with lung cancer have advanced disease at presentation,6 and many of these have had symptoms for many months. Early diagnosis, awareness of warning symptoms and prompt referral are therefore major healthcare priorities.
In its original guidance in 2005, NICE stated that the public needs to be better informed of the symptoms and signs of lung cancer, through co-ordinated campaigning to raise awareness and that it was important to ensure that patients have the best chance of early diagnosis by prompt attention to warning symptoms.
The 2007 Cancer Reform Strategy7 included recommendations for early diagnosis and awareness, and established the National Awareness and Early Diagnosis Initiative (NAEDI). This is a partnership between the Department of Health, the National Cancer Action Team, and Cancer Research UK. NAEDI co-ordinates and provides support to activities and research that promote the earlier diagnosis of cancer.8
Late diagnosis in lung cancer is of major concern and pilot projects in the Midlands to raise public awareness began in October 2011 with £1.5 million funding. About 40% of rapid access/two-week wait referrals for suspected lung cancer have the diagnosis confirmed, a proportion far higher than for many other cancers.9
The updated NICE guidelines retain the 2005 recommendations on awareness, early diagnosis and referral, see box 1, above, for referral criteria. There are unpublished data that indicate wide variations in the use of chest X-ray and rates of rapid access referral. The difficulty is that many other conditions can cause some of the symptoms and warning symptoms may recur. However, if we are to improve outcomes in lung cancer, more patients need to be sent for chest X-ray and referred urgently, where appropriate. If the chest X-ray is normal but there is a high suspicion of lung cancer the patient should still be referred urgently (see box 1, left).
Diagnosis and staging
The new NICE guideline contains a diagnostic and staging algorithm. This was developed following a review of the evidence for accuracy and safety of the investigations combined with a detailed cost-effectiveness analysis to determine the best sequence. The starting point for the respiratory physician is the clinical assessment and CT scan. From then on the principle is to choose investigations that give the most information about diagnosis and staging with least risk to the patient.
In addition, as modern targeted chemotherapy requires knowledge of tumour subtype and markers that predict response to chemotherapy, diagnostic and staging samples must be of sufficient quality for this purpose.
Non small cell lung cancer
Treatment with curative intent
For treatment with curative intent to be successful the fitness of the patient also needs to be accurately assessed. Three recent evidence-based guidelines, from NICE,6 the BTS and the Society for Cardiothoracic Surgery in Great Britain and Ireland,10 and the ERS/ESTS,11 respectively, inform this approach.
Stage and fitness need to be considered together. More advanced stage disease requires better fitness for the more extensive surgery whereas early stage disease may permit curative treatment by lung-sparing surgery or radiotherapy, see figure 1, p19.
For fitness assessment a trimodality approach is recommended. Risk should be calculated for:
• operative mortality, using risk scores
• cardiovascular morbidity, with active intervention if indicated
• postoperative dyspnoea, assessed by lung segment counting, lung function and, if borderline, exercise testing
To ensure that all patients have the best chance of being offered curative treatment, patients should be re-assessed by the surgeon and/or radiation oncologist after any optimisation (see figure 2, opposite). Patients should be encouraged to stop smoking, as this is known to reduce postoperative complications, but surgery should not be postponed.
Surgery that minimises loss of lung tissue is recommended, including segmentectomy, or for more advanced disease, bilobectomy (rather than pneumonectomy which should be avoided where possible). The latest radiotherapy techniques such as stereotactic body radiotherapy (SBRT) that minimise dose to normal lung are encouraged although research evidence is not yet mature. Combination treatment, where fitness allows, is also encouraged as there is evidence that outcomes are improved. Adjuvant chemotherapy after surgery is recommended if stage is N1 or later or the primary tumour is ≥4cm diameter.
Chemotherapy
Chemotherapy for non small cell lung cancer (NSCLC) was not part of the NICE 2011 guideline update as there are several published technology appraisals: TA162 erlotinib,12 TA181 pemetrexed,13 and TA192 gefitinib.14 This area is likely to change in the future, but currently platinum doublets are offered with pemetrexed for non-squamous tumours (epidermal growth factor receptor (EGFR) mutation –ve) and with gemcitabine, docetaxel, vinorelbine or paclitaxel for squamous tumours. Patients with non-squamous EGFR +ve tumours are offered gefitinib.
Small cell lung cancer
SCLC is an aggressive form of lung cancer and can progress quickly, reducing performance status and making successful treatment less likely. Thus one of the key recommendations is to arrange an assessment by a thoracic oncologist within one week of deciding to recommend treatment.
For the minority of patients with limited stage disease (tumour can be completely encompassed by a radiotherapy volume) outcomes can be remarkably good and so there are recommendations for concurrent chemoradiotherapy, where fitness allows. Surgery should be considered where tumours are ≤3cm diameter without nodal disease.
For all SCLC, prophylactic cranial irradiation should be given where there is no disease progression on first-line treatment and second-line treatment offered on progression, but there is doubtful benefit of the latter if there has been no response to first-line treatment. NICE TA184 addresses the use of topotecan for the treatment of relapsed SCLC.15
Endobronchial obstruction
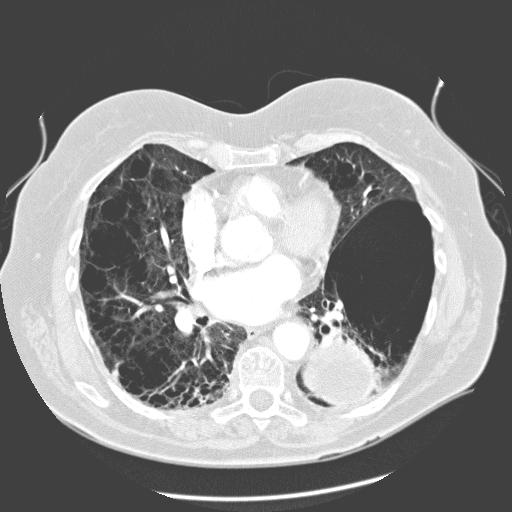
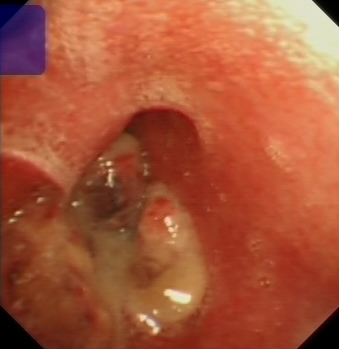
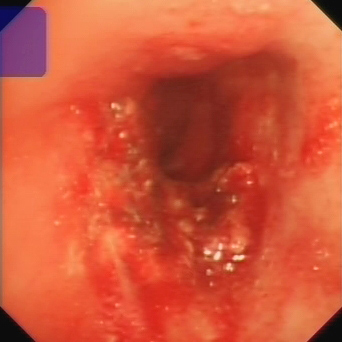
Many patients have large airway involvement and while this may respond to chemotherapy and radiotherapy, it may not, or may relapse, causing distressing symptoms related to lobar and pulmonary collapse. While the evidence is mainly in the form of case series, there is no doubt that patients gain symptomatic benefit from having a main or lobar bronchus cleared (see figure 3). This is best done early on, so if patients have large airway involvement they should be monitored clinically and radiologically for endobronchial obstruction to ensure treatment is offered promptly.
Communication
Successful communication of often complex issues requires both good communication skills and in-depth knowledge. It is important to find out what the patient knows and to provide accurate and clear verbal and written information at appropriate times, and support patients as they receive information. NICE recommends tailor-made decision aids. Discussions should be clearly documented and patients offered a copy. All information should be shared between healthcare professionals, including any advanced decision.
If the patient does not wish to confront issues, this should be respected. NICE also recommends that a lung cancer clinical nurse specialist is available at all stages of care to support patients and carers.
Follow-up
NICE found that patients who were not given regular follow-up appointments were more likely to use emergency services for uncontrolled symptoms. Thus all patients should be offered an initial specialist follow-up appointment within six weeks of completing treatment to discuss ongoing care and offered regular appointments thereafter (which can be integrated care).
Patients and relatives often wish to discuss issues with their GP throughout the pathway and the GP can help improve their understanding. Regular attendance at the practice may serve to identify troublesome symptoms early as well as detecting the development of anxiety and depression. It is important not to rely on patients requesting appointments when they experience symptoms. Ideally, protocol-driven follow-up by a lung cancer clinical nurse specialist should be available.
Symptoms to look for are mainly those of advancing cancer. Those suggestive of metastatic disease such as pain or weight loss are best identified and treated as early as possible. Patients with endobronchial obstruction may experience lower respiratory infections, progressive dyspnoea or pain due to lung collapse. Again, early treatment may improve quality of life considerably.
Conclusion
It is important that all healthcare professionals and patients understand that a modern approach to early presentation, assessment and treatment can improve survival and mortality. In secondary care the challenge is to ensure the same high standards of care found in some UK centres and abroad, that are achieving better survival and higher curative treatment rates, are applied universally. Considerable progress is being made with greater access to diagnostic and staging investigations, more thoracic surgeons and more modern radiotherapy equipment.
For primary and integrated care the challenges are to promote public awareness and respond promptly to warning symptoms, particularly persistent cough, extending this to include more patients and resulting in greater numbers of referrals for imaging or rapid access clinic assessments.
REFERENCES
References
1 www.info.cancerresearchuk.org/cancerstats/mortality
2 The NHS Information Centre. National Lung Cancer Audit 2010. IC03020211
3 Rich AL, Tata LJ, Free CM et al. Inequalities in outcomes for non-small cell lung cancer: the influence of clinical characteristics and features of the local lung cancer service. Thorax 2011 Jul 23. [Epub ahead of print]
4 Rich AL, Tata LJ, Free CM et al. How do patient and hospital features influence outcomes in small-cell lung cancer in England? Br J Cancer 2011;105:746-752
5 Coleman MP, Forman D, Bryant H et al. Cancer Survival in Australia, Canada, Denmark, Norway, Sweden, and the UK (the International Benchmarking Partnership): an analysis of population-based cancer registry data. Lancet 2011;377:127-38
6 National Institute for Health and Clinical Excellence. CG121. Lung cancer: The diagnosis and treatment of lung cancer (Update). NICE. London. 2011
7 Department of Health. Cancer Reform Strategy. 2007
8 www.ncri.org.uk/default.asp?s=1&p=5&ss=11
9 Lewis NR, Le Jeune I, Baldwin DR. Under utilisation of the 2-week wait initiative for lung cancer by primary care and its effect on the urgent referral pathway. Br J Cancer 2005; 93:905-908
10 Lim E, Baldwin DR, Beckles M et al. British Thoracic Society and the Society for Cardiothoracic Surgery in Great Britain and Ireland Guidelines on the Radical Management of Patients with Lung Cancer. Thorax 2010;65(suppl III):iii1-iii27
11 Brunelli A, Charloux A, Bolliger CT et al. ERS/ESTS clinical guidelines on fitness for radical therapy in lung cancer patients (surgery and chemo-radiotherapy). Eur Resp J 2009;34:17-41
12 National Institute for Health and Clinical Excellence. TA162. Erlotinib for the treatment of non-small-cell lung cancer. NICE. London. 2008
13 National Institute for Health and Clinical Excellence 2009. TA181. Pemetrexed for the first-line treatment of non-small-cell lung cancer. NICE. London. 2009
14 National Institute for Health and Clinical Excellence 2010. TA192. Gefitinib for the first-line treatment of locally advanced or metastatic non-small-cell lung cancer. NICE. London. 2010
15 National Institute for Health and Clinical Excellence 2009. TA184. Topotecan for the treatment of relapsed small-cell lung cancer. NICE. London. 2009
USEFUL INFORMATION
NICE CG121. Lung cancer: The diagnosis and treatment of lung cancer
Macmillan Cancer Support
tel: 0808 808 00 00 (Mon-Fri: 9am-8pm)
ARTICLE IN PDF
 Download this article in PDF format
CLICK ON IMAGES
EXTERNAL WEBLINKS
NICE
Recent evidence
Lung
British National Formulary
Malignant disease and immunosuppression
NCI
Supportive and palliative care
NICE
PubMed
Lung cancer improving outcomes
UK Risk Assessment Tools
QCancer
Qcancer men
Qcancer women
UK Early diagnosis programmes
UK NCAT
Macmillan - early diagnosis