SEARCH

Tibbott R, Clark A, Diagnosing and managing peanut allergy in children. Practitioner 2014;258 (1772):21-24
Diagnosing and managing peanut allergy in children
23 Jun 2014
AUTHORS
Dr Rebecca Tibbott MBBS BSc MRCPCH, Academic Clinical Fellow Paediatric Allergy
Dr Andrew Clark MBBS MD MRCPCH,Consultant Paediatric Allergist
Allergy Department, Addenbrooke’s Hospital, Cambridge University Hospitals, NHS Foundation Trust, Cambridge, UK
Article
Peanut allergy is a common disease and is becoming an increasing public health burden.
Sensitisation to peanut in the general UK population is around 3%. This translates to clinical allergy in around 1%, with 1 in 70 children in the UK affected.1 The prevalence is thought to be rising.1 Accidental exposures are frequent 2,3 and nut allergies are the leading cause of fatal food allergic reactions.4
Mechanism
Allergic reactions to peanuts are nearly always an immediate, type 1-mediated hypersensitivity response. Reactions arise due to the formation of IgE antibodies as a result of prior sensitisation to peanut proteins. On first exposure, the peanut protein antigen is processed by an antigen presenting cell. Binding of the antigen to a T cell leads to activation and crosstalk between T and B cells resulting in the production of peanut-specific IgE antibodies.
These circulating antibodies bind to the surface of mast cells and basophils via their IgE receptors. On re-exposure to peanut protein, the effector cells degranulate, leading to the release of pre-formed granules containing histamine, tryptase and leukotrienes.
The typical physiological response associated with a type 1-mediated hypersensitivity reaction, e.g. smooth muscle contraction, mucous secretion, and vasodilatation, are driven by these mediators. These responses are typically rapid in onset and can lead to systemic effects i.e. anaphylaxis.
The initial route, dose, frequency and duration of peanut sensitisation is often not known.
Children react on what is apparently their first exposure. Therefore, it has been postulated that sensitisation may occur through one of several different routes: in utero;5 through breast milk;6 in eczematous children through a compromised skin barrier;7 or through low-dose environmental exposure e.g. inhalation.8
Presentation
Peanut allergy most commonly presents in the first five years of life. More than 90% of nut allergic children will have a history of eczema, asthma, rhinitis or another food allergy e.g. egg or other nuts.
Typical symptoms and signs of IgE-mediated reactions to peanut are described in table 1. Symptoms develop within minutes of exposure.
This list is not exhaustive and symptoms of allergic reactions in children can sometimes be more subtle as they are less able to describe their symptoms.
A change in behaviour, for example, becoming quiet or distressed can signify the onset of an allergic reaction. A persistent cough, change in voice or drooling suggest laryngeal involvement. Children may also spit out the offending food or refuse to eat it.
Diagnosis
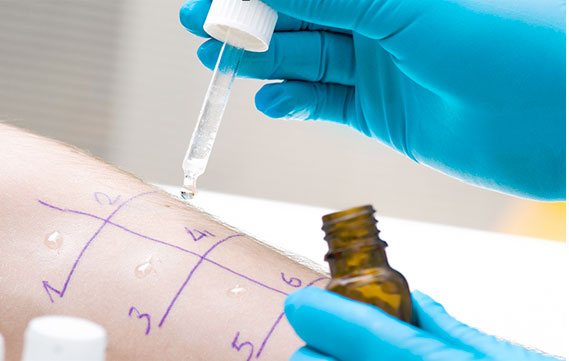
The clinical diagnosis of peanut allergy is made from a typical history in combination with clinical evidence of sensitisation i.e. the presence of peanut-specific IgE. Tests for specific IgE should only be carried out if there is a strong suspicion of allergy from the history, see figure 1. Importantly, positive skin prick tests or positive serum specific IgE demonstrate sensitisation to a specific allergen, but alone are not proof that the allergen is the cause of the clinical symptom. The specificity of both tests depends on the clinical history taken prior to the testing, the pre-test probability.
Traditionally, a skin prick test wheal ≥ 3 mm or specific IgE > 0.35kU/l are used to support a diagnosis of peanut allergy. Some studies have suggested various decision points above which the positive predictive value for the skin prick test and specific IgE are diagnostic of peanut allergy, even in the absence of a positive history. These vary between populations studied.9
Irrespective of the value of a positive skin prick test or serum specific IgE, it is important to remember that the magnitude of the result does not reflect the severity of a future reaction. No test is helpful for screening e.g. in siblings of peanut-allergic children.
Component resolved diagnostics may be used by specialists if additional information is required, for example if the history is not clear.
Major components in peanut allergy include Ara h 1, 2, 3, and 6 which are seed storage proteins associated with primary allergy to peanut. They are present in large amounts, heat stable and resistant to gastric digestion. The presence of Ara h 2-specific IgE suggests primary peanut allergy with the potential for more severe reactions.10 Food challenges can be performed in cases of uncertainty but are often unnecessary.
Prognosis
In studies, approximately 20% of peanut allergic children are thought to outgrow their peanut allergy.11
In practice, however this number is much lower. Peanut allergy is rarely outgrown in older children and adults.12
Accidental exposure is commonplace with the greatest risk being in teenagers and young adults, where there is less adult supervision and an increase in risk-taking behaviour e.g. drinking alcohol.
While allergy testing cannot predict the magnitude of a reaction, there are several predictors of future severe reactions, including:
• Poorly controlled asthma
• Multiple allergies
• Previous severe reactions4
Patients are often told that their reactions will worsen with each subsequent accidental exposure – this is not true. The amount of peanut consumed is likely to be the major determinant of severity on each occasion. There are thought to be several extrinsic factors that can change the threshold at which an allergic patient will react, including intercurrent illness, sleep deprivation and exercise.13
Management
Management consists of a comprehensive package of allergen avoidance advice, provision of emergency medication, family and school/nursery training. Because of the complexity and time involved, allergy specialists are best placed to provide this, but the process should begin in primary care before referral.
The mainstay of management is advice on allergen avoidance. Verbal and written advice should be given. Children and their carers should be educated in the recognition and treatment of allergic reactions and a written management plan should be provided.
Fast-acting antihistamines as well as adrenaline autoinjectors should be provided as appropriate, see table 2.14 Training on the use of adrenaline autoinjectors should be provided at diagnosis and retraining should occur at each follow-up appointment.
The latest MHRA recommendations on adrenaline autoinjector use for patients are summarised in table 3, above. Undertreated asthma is a known risk factor for severe reactions and therefore patients with co-existent asthma should undergo regular review.
Primary care
In addition to gathering evidence from a thorough clinical history to support the diagnosis, management of peanut allergy in primary care is five fold:
• Avoidance advice: Initial advice should be provided. Food labels should be checked for peanut in the ingredients and avoided if present. Food with product advisory labels (e.g. ‘this may contain traces’) should be avoided if high risk (e.g. snack food such as chocolate, cakes or biscuits)
• Antihistamine provision for mild reactions
• Adrenaline autoinjector provision if appropriate (see table 2) and training
• Asthma review
• Allergy services referral
Future therapies
Novel therapies such as oral immunotherapy aimed at reducing reactivity to peanut and tree nut are emerging.
Peanut oral immunotherapy can successfully induce desensitisation in a large proportion of peanut allergic children.15 However, the procedure is time consuming, allergic reactions during treatment occur and further studies are required before this is widely available.
REFERENCES
1 Grundy J, Matthews S, Bateman B et al. Rising prevalence of allergy to peanut in children. J Allergy CIin Immunol 2002;110:784-9
2 Ewan PW, Clark AT. Efficacy of a management plan based on severity assessment in longitudinal and case-controlled studies of 747 children with nut allergy: proposal for good practice. Clin Exp Allergy 2005;35(6):751-756
3 Yu JW, Kagan R, Verreault N et al. Accidental ingestions in children with peanut allergy. J Allergy Clin Immunol 2006;118(2):466-472
4 Bock SA, Muñoz-Furlong A, Sampson HA. Fatalities due to anaphylactic reactions to foods. J Allergy Clin Immunol 2001;107:191-3
5 Fox A, Sasieni P, du Toit G et al. Household peanut consumption as a risk factor for the development of peanut allergy. J Allergy Clin Immunol 2009;123:417-23
6 Vadas P, Wai Y, Burks W et al. Detection of peanut allergens in breast milk of lactating women. JAMA 2001;285:1746-8
7 Brown SJ, Asai Y, Cordell HJ et al. Loss-of-function variants in the filaggrin gene are a significant risk factor for peanut allergy. J Allergy Clin Immunol 2011;127(3): 661-7
8 Trendelenburg V, Ahrens B, Wehrmann AK et al. Peanut allergen in house dust of eating area and bed
– a risk factor for peanut sensitization? Allergy 2013;68:1460-1462
9 National Institute for Health and Clinical Excellence. CG116. Food allergy in children and young people. NICE. London. 2011
10 Nicolaou N, Poorafshar M, Murray C et al. Allergy or tolerance in children sensitized to peanut: prevalence and differentiation using component-resolved diagnostics J Allergy Clin Immunol 2010: 125:191-7
11 Skripak JM, Wood RA. Peanut and tree nut allergy in childhood. Pediat Allergy Immunol 2008; 19:368-73
12 Bock SA, Atkins FM. The natural history of peanut allergy. J Allergy Clin Immunol 1989;83:9004
13 www.tracestudy.com
14 Muraro A, Roberts G, Clark A et al. The management of anaphylaxis in childhood: position paper of the European Academy of Allergology and Clinical Immunology. Allergy 2007;62(8):857-71
15 Anagnostou K, Islam S, King Y et al. Assessing the efficacy of oral immunotherapy for the desensitisation of peanut allergy in children (STOP II): a phase 2 randomised controlled trial. Lancet 2014;383:1297-304
ARTICLE IN PDF
 Download this article in PDF format
PRESET SEARCHES
PubMed
NICE evidence search
Immediate CPD prompts
These handy templates*, associated with all articles, prompt drafting of personal learning, reflection and planning.
Save your record straight into your personal development folder on your device or cloud storage system.
*Adobe fillable PDFs. Adobe reader needed for iPad
Comment or question
If you, or your peer group, would like to comment on an article or have a question for the authors, write to:
Editor
EXTERNAL WEBLINKS
Anaphylaxis Campaign
Helpline: 0125 254 2029
Allergy UK
Helpline: 0132 261 9898
British Society for Allergy & Clinical Immunology