SEARCH

The Practitioner 2010; 254 (1732): 24-26
Tracking down chlamydia infection in primary care
21 Sep 2010
Article
Chlamydia, caused by the D-K serovars of Chlamydia trachomatis, is the most commonly diagnosed bacterial sexually transmitted infection in this country.1
In 2008, the total number of diagnoses made in the UK was 214,033.2
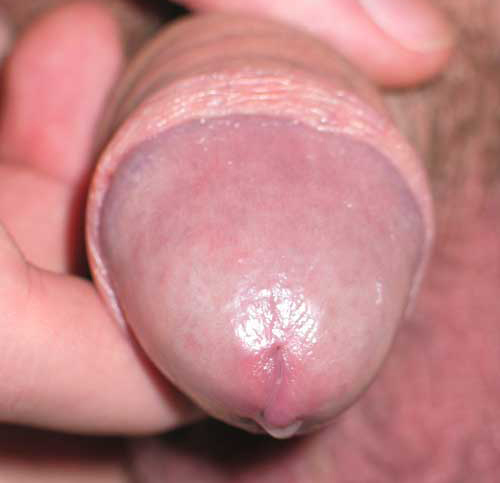
Symptoms and signs which suggest chlamydia infection are shown in table 1, however infection is usually asymptomatic. Sexually active people aged under 20 are the group most likely to have a positive result if tested. This is probably because this group changes partners more frequently. However, there also appear to be immunological factors which make infection more persistent in the young. Transmission occurs through vaginal, rectal or oral sex. It can also be vertically transmitted.
Untreated chlamydia infection can result in complications including pelvic inflammatory disease (potentially leading to infertility or ectopic pregnancy), sexually acquired reactive arthritis and epididymo-orchitis. However, there is controversy over important questions such as the likelihood of complications developing and, hence, what sort of control measures are appropriate. Some countries, for example England, have set up screening programmes while others, such as Scotland, have elected not to. A useful supplement covering these issues has recently been published by The Journal of Infectious Diseases.3
Detailed guidelines on the management of chlamydia have been produced by the British Association for Sexual Health and HIV (BASHH) and, more recently, by SIGN. 4,5
Testing
The guidelines recommend that the following groups should be offered testing for chlamydia:
- Sexually active individuals with symptoms or signs suggestive of chlamydia infection (see table 1, above)
- People in certain risk groups or in circumstances where it is particularly important to make the diagnosis (see table 2)
Early detection and treatment can prevent onward transmission. However, it is unclear what effect early treatment has on the chance of complications developing.
Most laboratories use a nucleic acid amplification test (NAAT) of which there are a variety of different versions, all with similar, and very good, performance. Older methods such as enzyme immunoassay or direct immunofluorescence have largely been abandoned.
In heterosexual men, a first voided urine (FVU) sample is the specimen of choice. Here, the first 20 ml of urine is passed into a plain universal container. Men should hold the urine for at least one hour before providing the specimen. Women who are not undergoing speculum examination can provide either an FVU or a self-obtained low vaginal swab (SOLVS). Some NAATs work better with SOLVS so it is a good idea to check with your lab to see which they prefer. In women undergoing speculum examination, either a vaginal or an endocervical swab obtained during the procedure can be submitted.
Rectal, pharyngeal or conjunctival swab specimens can also be obtained. Although widely used in clinical practice there are limited data available on the validity of NAATs for evaluating specimens from these sites. Again, it is worth checking with your local lab to find out whether they accept these specimens.
Recently, there has been a re-emergence of lymphogranuloma venereum (LGV), an ulcerative STI caused by the L1-3 serovars of
C. trachomatis. Since 2003, 99% of cases of LGV in the UK have occurred in men who have sex with men. It can be transmitted by vaginal sex as well but in the UK this does not appear to be a common mode of transmission.6 If the patient has rectal symptoms such as pain, tenesmus or bleeding, then indicate this on the request form and ask the lab to test for LGV. If the rectal specimen is positive for chlamydia then the lab will forward it to the reference laboratory for genotyping.
Tests for other STIs such as gonorrhoea, HIV and syphilis should be offered, based on risk assessment and clinical judgement.
Treatment
Uncomplicated genital or pharyngeal infection
Azithromycin 1 g orally given as a single dose is the drug of choice.
Rectal infection
Asymptomatic rectal chlamydia infection may be treated with azithromycin 1 g orally as a single dose. However, concerns have been expressed as to the effectiveness of this regimen and some authorities recommend doxycycline 100 mg bd for two weeks.
Chlamydia in pregnancy
Again, azithromycin 1 g orally is recommended for the treatment of uncomplicated infection. Such usage is off licence and this should be explained to the patient. An alternative regimen is erythromycin 500 mg qds for seven days.
Chlamydial epididymo-orchitis
Doxycycline 100 mg bd for 14 days.
Pelvic inflammatory disease
Doxycycline 100 mg bd for 14 days plus metronidazole 400 mg bd for
14 days.
It is important to note that it is not generally possible to exclude
Neisseria gonorrhoeae as an additional/alternative organism until results are available. Therefore guidelines recommend covering for this, for example, by giving ceftriaxone 250 mg im once.
Other management
The following steps should also be taken:
- All patients with chlamydia and their sexual partners should be advised to abstain from sexual contact until treatment has been completed. If azithromycin is used, they should abstain for seven days following treatment
- Patients should receive written information about their condition
- Sexual contacts should be notified
- Relevant health promotion should be carried out including the provision of condoms and screening for hazardous drinking.
Partner notification
Identifying sexual contacts and treating them is a vital, although often neglected, aspect of chlamydia management. Contacts can be identified and informed by the patient or by healthcare staff. Partner notification should be offered to all patients with chlamydia regardless of where they were diagnosed: hospital ward, pharmacy, general practice, sexual health clinic or by postal testing kit. Models of partner notification currently used in the UK include:
- Centralisation of the process whereby positive tests from any setting are forwarded to the local GUM clinic or chlamydia screening office
- Written referral to a GUM clinic
- Notification of partners by practice nurses with the support of GUM health advisers if needed
There is no evidence that one approach is better than the others. The main reasons why partners fail to be informed are because the notification process is never actually initiated or the patient does not have sufficient details about their contacts to be able to trace and inform them. All contacts should be offered a test for chlamydia and advised to take treatment
(1 g azithromycin) without waiting for results. If a test proves positive, a new round of partner notification should take place. Treating contacts at first visit means that problems arising from false-negative results and failure to reattend are avoided. If individuals decline treatment, they should be advised to abstain from sex until they have had a negative chlamydia test.
Look-back period
In the case of symptomatic men, all sexual partners going back to four weeks before the onset of symptoms, or the last sexual partner, should be notified. In the case of asymptomatic men, and all women, all sexual contacts in the six months before presentation should be notified.
Follow up
Guidelines recommend that patients should be followed up two to four weeks after treatment.
This will help to check compliance, to tie up loose ends with respect to partner notification and to reinforce health promotion messages. Telephone follow-up is more cost-effective and convenient than face-to-face interview.
Test of cure
Test of cure is routinely recommended only in pregnant patients in whom the standard treatment may be suboptimal. Some experts believe that, due to increased volume of distribution, treatment may be less effective in this group.
However, test of cure may have a role in other situations such as reassuring an anxious patient or in the case of suspected noncompliance or re-infection. Since NAATs can remain positive up to five weeks after completion of treatment, testing should be repeated only after that period. Re-infection rates as high as 30% have been found in certain test settings.7 Therefore a test for re-infection is advised three months to one year after treatment.
Referral
Uncomplicated chlamydia infection can be managed in primary care, as described above, with support from GUM for partner notification where needed. Support from relevant specialists should be sought, if required, for managing complications such as pelvic inflammatory disease or arthritis.
REFERENCES
1 Health Protection Agency. Chlamydia. www.hpa.org.uk/
Publications/InfectiousDiseases/Factsheets/factChlamydia
2 Health Protection Agency. Number and rates of new diagnoses of genital chlamydia diagnoses made in any setting, by gender and age-group in the UK, England and English SHAs: 2008-2009. www.hpa.org.uk/web/HPAwebFile/HPAweb_C/1281953080247
3 Gottlieb SL, Martin DH, Xu F et al. Summary: The natural history and immunobiology of Chlamydia trachomatis genital infection and implications for Chlamydia control. J Infect Dis 2010 Jun 15; 201 Suppl 2:S190-204
4 Horner PJ, Boag F. 2006 UK National guideline for the management of genital tract infection with chlamydia trachomatis. www.bashh.org/documents/61/61.pdf
5 Scottish Intercollegiate Guidelines Network. SIGN 109. Management of genital chlamydia trachomatis infection. SIGN. Edinburgh. 2009
6 www.hpa.org.uk/web/HPAwebFile/HPAweb_C/1245581513523
7 LaMontagne D S, Baster K, Emmett L et al. Incidence and reinfection rates of genital chlamydia infection among women aged 16-24 years attending general practice, family planning and genitourinary medicine clinics in England: a prospective cohort study in the Chlamydia Recall Study Advisory Group. Sex Transm Infect 2007; 83: 292-303
ARTICLE IN PDF
 Download this article in PDF format
EXTERNAL WEBLINKS
PubMed
NICE Evidence