SEARCH

Practitioner 2009;253 (1723):27–30
HIV testing in primary care will help improve early diagnosis
15 Nov 2009
AUTHORS
Dr Adrian Palfreeman FRCP
Consultant physician, University Hospitals, Leicester
Dr Martin Fisher FRCP
Consultant physician, Brighton and Sussex University Hospital
Dr Ewen Stewart MRCGP
GP in Edinburgh and Chair of the RCGP Sex, Drugs and HIV group
Article
HIV is now a treatable medical condition and the majority of those diagnosed with the virus remain fit and well on treatment.
In all, 77,000 people are known to be infected with HIV in the UK. However, 28% are unaware of their infection and are therefore unable to access treatment.1 They are also at risk of unwittingly passing the virus on to others.
Late diagnosis is the most important factor associated with HIV-related morbidity and mortality in the UK.2 Many patients who present late to care have been to see their GP in the months or years leading up to their diagnosis but have never been tested for HIV. 3,4
National guidelines on HIV testing have recently been published by the RCP to help improve provision and uptake of HIV testing in both primary and secondary care settings.5 These guidelines have been developed with input from various royal colleges, including the RCGP, specialist societies and the GMC, and have been adopted by the Department of Health.
Who should be tested?
The guidelines recommend that GPs should offer an HIV test (see box 1, p29) to patients:
- from communities or geographical locations where HIV is common
- who present with a medical condition in which HIV might be implicated. 5
- with a medical condition compatible with AIDS or with any HIV indicator disease (see table 1, p28).
Offering testing to patients with these conditions should lead to fewer missed late diagnoses. For patients to benefit from optimally timed intervention with antiretroviral therapy they must be diagnosed before they fall ill.
The guidelines recommend that HIV testing should be routinely offered to certain groups of patients whenever they present in primary care, see table 2, p28.
New patients
GPs should also consider offering an HIV test to new patients who register with the practice in areas where diagnosed HIV prevalence in the local population (PCT/LA) exceeds 2 in 1,000 population (see local PCT data). This population-based screening approach is currently being evaluated in several sites in a pilot scheme funded by the DH.
Although the most modern HIV tests can detect HIV infection much earlier than previously, in very recent infection - when patients may be most symptomatic - the tests may be negative. In this situation, if primary HIV infection (PHI) is suspected, either urgent referral to specialist services
(a GU clinic or HIV service) or a repeat test in seven days is recommended.
HIV viral load testing can be used, but it is recommended that this is only performed with specialist input.
Pre-test discussion
The main purpose of pre-test discussions is to establish informed consent for HIV testing. Lengthy,
pre-test HIV counselling is not usually necessary unless a patient requests or needs this. You are likely to do more harm by not testing than by testing. The essential elements that the pre-test discussion should cover are:
- an explanation of why the test is recommended e.g. routine or clinically indicated
- the benefits of testing to the individual
- details of how the result will be given (who, when and where).
- confidentiality. Emphasise confidentiality and answer any questions that the patient may have
- informed consent. Once this has been obtained you should record it in the notes.
A simple explanation such as ‘an HIV test is now part of the routine care of all patients with your condition in order not to overlook this treatable medical condition' may be helpful. This approach has been successful in GU and antenatal clinics and is generally acceptable with uptake rates of over 95%. 1
If a patient refuses a test the reasons should be explored to ensure that their decision has not been based on erroneous beliefs about the virus or the consequences of testing. If implications for either insurance or criminal prosecution for transmission are raised by the individual as reasons for not testing these should be further explored and any factual inaccuracies corrected.
Life assurance and mortgage issues should not be a deterrent to testing as negative test results should have no impact and should not be supplied to insurance companies.6 It is important to be vigilant for computer-generated medical reports that may contain this information.
Certain groups of patients e.g. children, people with learning disability or mental health problems may require additional support and referral for full counselling before testing. However, these patients are the exception not the rule.
Repeat testing
The need for a repeat HIV test, if the patient is still within the window after a specific exposure, should be discussed. Although modern fourth-generation tests shorten the time from exposure
to seroconversion a repeat test at
3 months is still recommended to exclude HIV infection definitively.
Occasionally, HIV results are reported as reactive or equivocal. These patients may be seroconverting (see below) and management of re-testing may be complex. These individuals should be promptly referred to specialist care.
Post-test discussions
HIV-positive patients
As in any situation where bad news is being given, the result should be presented clearly, face to face, in a confidential environment. It is essential to find out about local specialist services and to have established a clear pathway for onward referral before giving the patient their results.
National standards recommend that all patients should be seen by a specialist within two weeks, however, in practice most centres will fit a newly diagnosed patient into the next clinic and they will be seen within 48 hours.
More detailed post-test discussions (including assessment of disease stage, consideration of treatment, and partner notification) will be performed by the GUM/HIV specialist team.
HIV-negative patients
The need for a repeat HIV test, if the patient is still within the window after a specific exposure, should be discussed. Although tests have improved greatly a repeat test at 3 months is still recommended to exclude HIV infection.
Equivocal results
Occasionally HIV results are reported as reactive or equivocal. These patients may be seroconverting (see section on primary HIV infection, below) and management of re-testing may be complex. These individuals should be promptly referred to specialist care.
GPs should consider offering a repeat HIV test to anyone who remains at continuing risk of infection particularly annual testing of men who have sex with men and use testing as an opportunity to give advice on prevention of future risk.
Primary HIV infection
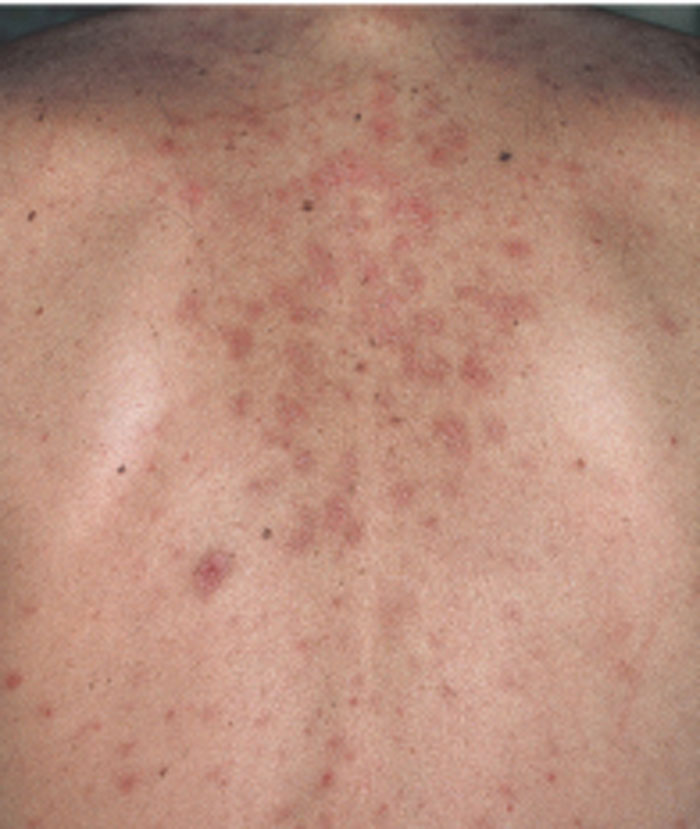
PHI or seroconversion illness occurs in around 80% of individuals, typically 2-4 weeks after infection. It is well recognised that this represents a unique opportunity to prevent onward transmission as an individual is considerably more infectious at this stage. Furthermore, this may be the only clinical opportunity to detect HIV before advanced immunosuppression many years later.
It is known that the features of PHI are non-specific and that individuals often present to primary care but frequently the diagnosis is missed or not suspected.7
The typical symptoms include a combination of any of the following:
- fever
- rash (maculopapular)
- myalgia
- pharyngitis
- headache/aseptic meningitis.
These symptoms will resolve spontaneously within 2-3 weeks. Therefore, if PHI is suspected, this needs to be investigated at the time of presentation and not deferred.
HIV testing should be considered in any patient with these symptoms perceived to be at risk of infection. In primary care details of an individual's sexual risk may be difficult to ascertain, but a low threshold for offering a test should remain.
Long-term follow-up
Patients living with HIV may well now have a near-normal life expectancy with antiretroviral treatment. It is important to remember potential drug interactions when they present with other unrelated medical conditions. Good communication between hospital specialists and primary care is essential.ARTICLE IN PDF
 Download this article in PDF format