SEARCH

Orrell RW. Diagnosing and managing muscular dystrophy. Practitioner 2012;256 (1754):21-24
Diagnosing and managing muscular dystrophy
20 Sep 2012
AUTHORS
Dr Richard W Orrell BSc MD FRCP, Senior Lecturer in Clinical Neuroscience, UCL Institute of Neurology, London, UK and Consultant Neurologist, Royal Free Hospital, London, UK
Article
Muscular dystrophy refers to a range of muscle diseases caused by defects in muscle proteins, leading to death of the muscle cells, with loss of muscle tissue, and weakness. Muscular dystrophy may present at any age from perinatal to old age. The muscular dystrophies all have a genetic basis, although not all causes have been identified.
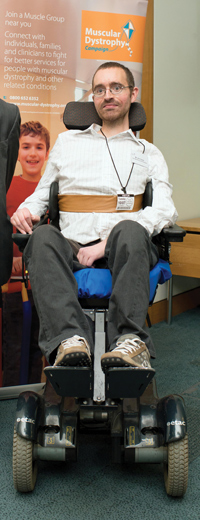
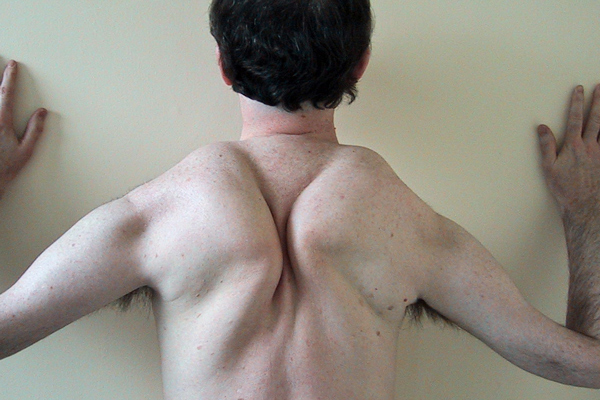
There are a wide range of muscular dystrophies, common examples are Duchenne muscular dystrophy1 (see figure 1), myotonic dystrophy,2 facioscapulohumeral dystrophy3 (see figure 2), limb girdle muscular dystrophy4 and congenital muscular dystrophies.5
Primary care presentation
Patients may present in primary care undiagnosed, or with a diagnosis and established disability when transferring practice.
The muscular dystrophies are rare conditions. Prevalence figures are imprecise, and depend on the diagnostic criteria applied, but there are increasing efforts to maintain registries of patients. For example the prevalence of myotonic dystrophy is 12:100,000; Duchenne muscular dystrophy 5:100,000 (incidence 1:3,500 male births); facioscapulohumeral dystrophy 4:100,000 (incidence 1:20,000); congenital muscular dystrophy 0.7:100,000.6
The development of clinical symptoms is usually gradual, and the earliest features may be difficult to identify and determine. With established disease the presence of muscle weakness and wasting is clear.
In children, the presentation may be delayed walking or poor performance in sporting activity. In children and adults presenting symptoms may include:
• difficulty raising from a squat
• difficulty raising from a chair
• difficulty lifting arms above the head
• poor balance
• drooping eyelids
• joint contractures
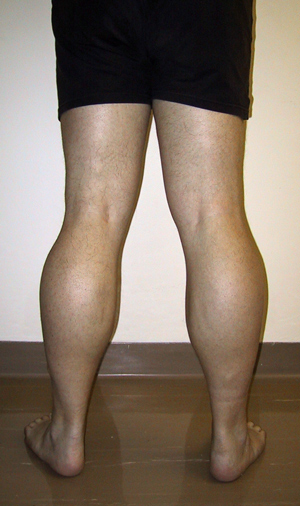
In some muscular dystrophies there may be a paradoxical appearance of muscle enlargement, as with calf hypertrophy (see figure 3).
Examination and assessment
Whatever the presentation, it is unlikely that the GP will be in a position to make a definitive diagnosis. Recognition that the patient has a muscle disease, with referral to appropriate hospital expertise is the key step. In the presence of slowly progressive muscle weakness and wasting, measurement of serum creatine kinase, showing elevation, would be a strong pointer to a muscle disease.
Retention of limb reflexes would favour a myopathy over a neuropathy. The diagnosis may be easier when other family members are already affected. Referral is usually to a paediatric or adult neurology service.
Confirming diagnosis
The major differential diagnosis is an inflammatory myopathy, such as polymyositis. This is an important distinction as this would be expected to respond to immunosuppressive treatment, for example, with prednisolone. Early diagnosis of an inflammatory myopathy is important to minimise muscle damage and to maximise recovery.
In the muscle clinic, physical examination may give a pointer to the diagnosis of muscular dystrophy.
For example, a limb girdle muscular dystrophy4 would typically affect shoulder and hip strength, and facioscapulohumeral dystrophy3 would affect muscles of the face and upper arm (see figure 2). Sometimes this may point immediately to an appropriate DNA blood test, and facioscapulohumeral dystrophy may be diagnosed in this way.
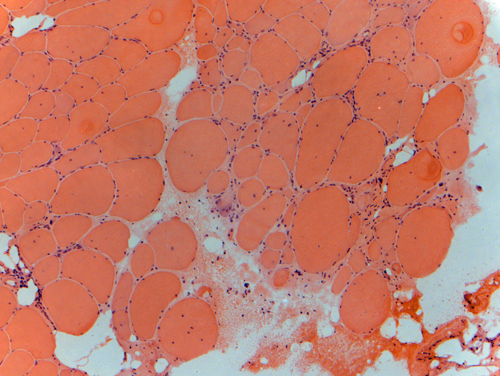
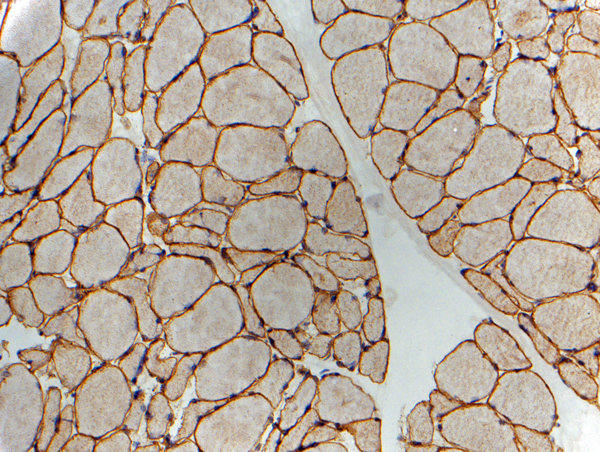
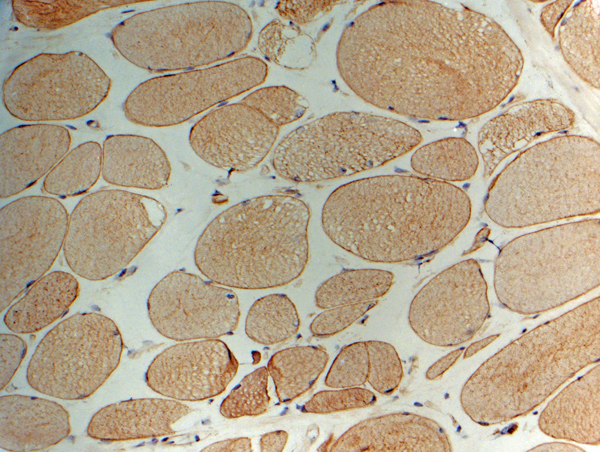
In more complex conditions a muscle biopsy may be performed. This is both to confirm the features of a muscular dystrophy (see figure 4), and also to identify the specific proteins involved (see figure 5). Muscle biopsy will identify patients with polymyositis, although there can be some confusion as patients with muscular dystrophy may also show inflammatory changes. EMG may have a role in identifying myopathy, and nerve conduction studies may distinguish between a myopathy and neuropathy.
Myotonic dystrophy2 is one of the more common muscular dystrophies, and unusual in that a dominant feature is the myotonia, that is a difficulty with muscle relaxation. Diagnosis is confirmed by DNA analysis, but EMG also shows diagnostic features of complex repetitive discharges (which sound like a dive bomber), and clinical examination will also show features of myotonia (typically slowness in relaxing a tight grip), together with the muscle wasting or dystrophy, in the limbs and facial muscles.
Myotonic dystrophy shows the hereditary feature of anticipation, that is the condition may appear to be more severe in successive generations. Typically the grandparent may have cataracts only, the parent an adult onset muscle stiffness with weakness, and the next generation presents with more aggressive muscle weakness in childhood, or in utero. Myotonic dystrophy is a multisystem disease, which may also affect cognition and behaviour, fertility, and insulin resistance.
Pompe disease is a rare inherited metabolic muscle disease, with defects in the acid alpha-glucosidase gene. Clinical presentation may be similar to a muscular dystrophy, especially limb girdle muscular dystrophy. There is now the possibility of treatment by enzyme replacement therapy.7 The diagnosis may be made on a blood spot test.
Genetics
The muscular dystrophies have a genetic basis, and it is often possible to identify the gene involved. Depending on the nature of the dystrophy, there may be important genetic issues to discuss with the family, including the possibility of prenatal diagnosis. The clinical genetics team would also be involved.
As other members of the family may also carry the gene, or have a similar condition, there may be a range of anxieties to address.
In Duchenne muscular dystrophy the inheritance is X-linked, with typically only boys being affected, the mother being an asymptomatic carrier.
Some limb girdle muscular dystrophies are autosomal dominant, but many are autosomal recessive affecting only one generation of a family.
Facioscapulohumeral dystrophy is autosomal dominant, passing from generation to generation.
Management
There is no curative therapy for the muscular dystrophies. In Duchenne muscular dystrophy prednisolone may be used to slow progression of the condition.8 This would be initiated and guided by the muscle clinic. Management directly related to the disease is usually provided in a multidisciplinary setting, including physiotherapy and occupational therapy, see table 1.9,10
There may be involvement of cardiac muscle, which may be assessed by echocardiography, and require pharmacological treatment. Cardiac conduction disturbance and arrhythmia may be initially assessed by ECG, and require pacemaker insertion.
Involvement of respiratory muscles may require respiratory support, including noninvasive ventilation, and occasionally invasive ventilation including tracheostomy.
Swallowing and feeding difficulty may require nutritional support, and possibly gastrostomy. Orthoses and orthopaedic management may also be needed.
Supporting patients and their families
The muscular dystrophies may cause significant disability in children, with considerable demands on the family. Social and educational support may be needed.
There may be recurrent crises, and prevention of crises, may include early recognition and treatment of chest infection.
In adults who develop symptoms of muscular dystrophy there are similar, but also different, issues including those related to work and relationships. Often the multidisciplinary services for adults are less well developed and less widely available than those for children.
Additional attention may be required by adolescents as their needs may be complex. A particular recognised difficulty is the transfer of management of patients with severe muscular dystrophy from paediatric to adult services, and special arrangements for transition have been developed and require support from the GP.
The GP may encourage the patient to attend a muscle clinic for appropriate review, including, for example, ongoing cardiac and respiratory assessment. Inappropriate emergency hospital admission is to be avoided if possible, and the GP may be key in ensuring implementation of complex care plans.
There is considerable research into the genetic mechanisms of the muscular dystrophies, and attempts at gene therapy11 and stem cell therapy,12 but with no useful therapy at present.
REFERENCES
1 Morrison LA. Dystrophinopathies. In: Muscular dystrophies. Handbook of Clinical Neurology. Eds Amato A, Griggs RC. Elsevier. Edinburgh. 2011;11-39
2 Foff EF, Mahadevan MS. Therapeutics development in myotonic dystrophy type 1. Muscle Nerve 2011;44:160-169
3 Orrell RW. Facioscapulohumeral dystrophy. In: Muscular dystrophies. Handbook of Clinical Neurology. Eds Amato A, Griggs RC. Elsevier. Edinburgh. 2011;101:167-180
4 Nigro V, Aurion S, Piluso G. Limb girdle muscular dystrophies: update on genetic diagnosis and therapeutic approaches. Curr Opin Neurol 2011;24:429-436
5 Mercuri E, Muntoni F. The ever-expanding spectrum of congenital muscular dystrophies. Ann Neurol 2012;72:9-17
6 Amato AA, Griggs RC. Eds. Muscular dystrophies. Handbook of Clinical Neurology. Elsevier. Edinburgh. 2011
7 Cupler EJ, Berger KI, Leshner RT et al. Consensus treatment recommendations for late-onset Pompe disease. Muscl Nerve 2012;45:319-333
8 Abdel-Hamid H, Clemens PR. Pharmacological therapies for muscular dystrophies. Curr Opin Neurol 2012;25:604-608
9 Bushby K, Finkel R, Birnkrant DJ et al. Diagnosis and management of Duchenne muscular dystrophy, part 1: diagnosis, and pharmacological and psychosocial management. Lancet Neurol 2010;9:77-93
10 Bushby K, Finkel R, Birnkrant DJ et al. Diagnosis and management of Duchenne muscular dystrophy, part 2: implementation of multidisciplinary care. Lancet Neurol 2010;9:177-189
11 Verhaart IEC, Aartsma-Rus A. Gene therapy for Duchenne muscular dystrophy. Curr Opin Neurol 2012;25:588-596
12 Tedesco FS, Cossu G. Stem cell therapies of muscle disorders. Curr Opin Neurol 2012;25:597-603
USEFUL INFORMATION
Muscular Dystrophy Campaign
www.muscular-dystrophy.org
Provides support to patients, families, carers and healthcare professionals. There are useful information sheets on the different muscular dystrophies online
Freephone information line: 0800 652 6352
ARTICLE IN PDF
 Download this article in PDF format
CLICK ON IMAGES